Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Saturday, February 4, 2023

Would I Do Anything Differently for My Bones? Would you?

Someone asked me recently if, knowing what I know today, I would do anything differently for my bones.


Knowing what I know today (16 years after my osteoporosis diagnosis), I would never have taken Fosamax, 70 mg, once weekly. I suffered from dizziness and vertigo and had to stop taking it after six months. 


I would still take strontium citrate because taking it has been a positive experience. I am still taking it 15 years later at the full dosage of 680 mg/day.


I will not take any of the osteoporosis drugs. The anabolic drugs are, therapeutically, a big step forward over the antiresorptive ones, but all the bone drugs come with many potential side effects.


The only other bone therapy I find acceptable is vitamin K2 (MK4) at 45 mg/day (15 mg taken three times per day). MK4 at this dosage is given by prescription in Japan and other Asian countries for osteoporosis. It is also said to be heart healthy. The only problem is it is hard in Western nations to find reliable information about how this therapy is working out. I do not know any Americans who have used this therapy over a protracted period of time. Anyway, it is my Plan B, in case I ever want to switch from SC. Another, more likely, possibility for my future is to reduce my SC dosage by one-third or one-half and add MK4 at 15 mg or 30 mg/day.


You may have noticed that I did not mention vitamin K2 (MK7). That is because I would never take it based on the reports of many people who say they experience nervousness, insomnia, and/or heart palpitations with even small doses of MK7. Also, I feel there is more evidence for the efficacy of MK4 than MK7 because MK4 has been used in Japan for osteoporosis for more than 20 years. 


What, if anything, would you do differently for your bones?


Sunday, December 25, 2022

Bone- and Heart-Healthy Yogurt Dip

Below is a recipe for a simple, tasty yogurt dip that my husband came up with. It has only three ingredients, four, if you like more salt than is provided by the cheese. Unlike most dips, this one is healthy for our bones and hearts. Plus, it is delicious. You can play around with the amounts of ingredients, leave out the garlic, or add dried onion or another ingredient of your choice. The possibilities are endless. 

1/2 cup fat-free Greek yogurt

2 tbsp. shredded parmesan cheese

1 tsp. dried minced garlic

pinch of salt, if desired


Thursday, September 8, 2022

TBS, Strontium, and Prof. Didier Hans

Prof. Didier Hans, PhD, MBA co-founded Med-Imaps SA in 2006 and became CEO of Medimaps Group in 2012. He currently drives the company’s global strategy, orientation and business objectives, and oversees its Quality Management framework and policies.He holds a PhD in Medical Physics and an Executive MBA from HEC Geneva. https://www.medimapsgroup.com/team/didier-hans/

One of Medimaps Group's products, TBS iNsight™ (Osteo), is an advanced imaging software application for bone densitometers (DXA). It provides a way to better predict a patient’s risk for bone fracture, to fine-tune therapy decisions, and to improve patient management.

TBS iNsight™ is a Medical Device that is CE 2797 marked & has been cleared to be sold in the US.


https://www.medimapsgroup.com/tbs-osteo/


I recently had the opportunity to ask Prof. Hans a question by email. He graciously answered. 


My question:


Will a TBS score be affected by the bone strontium effect, as the BMD by DXA scan is?


His answer, paraphrased and confirmed: 


In our study of TBS and strontium ranelate, TBS was less affected by the larger atomic number of strontium than the BMD was affected. So, the study showed that strontium improved bone microarchitecture. 

Beneficial Effects of Strontium Ranelate vs. Alendronate on TBS and Bone Architecture

The following abstract was published on Osteoporosis International (2012) 23: (Supplement 2):S85–S386. 

Abstract P471, Pages S266-S267

Didier Hans1, Marc-Antoine Krieg1, Olivier Lamy1, Dieter Felsenberg2
1
Lausanne University Hospital Center of Bone Diseases, Bone and Joints Department, Lausanne, Switzerland, 2Charité Campus Benjamin Franklin, Klinik und Poliklinik für Radiologue und Muklearmedizin, Berlin, Germany

Objective(s): Trabecular Bone Score (TBS, Med-Imaps, France) is an index of bone architecture independent of BMD calculated by quantifying local variations in grey level from anteroposterior spine DXA scan and reported to be associated with fracture in prior case-control and prospective studies1. We compared the effects of strontium ranelate (SrRan) and alendronate (ALN) on spine architecture patterns as assessed by TBS in women with postmenopausal osteoporosis.

Material & Methods: A post hoc analysis was performed on DXAs (Hologic and GE Lunar Devices) from 79 women out of 189 included in a double blind, double dummy study and randomized to SrRan 2 g/day or ALN 70 mg/week during 2 years2. Spine TBS parameters were assessed by TBS iNsight (v1.9) at the spine after 12 and 24 months of treatment. We applied ISCD rules for individual vertebrae exclusion independently for BMD and TBS, respectively. Since duplicate measurements were performed at baseline, precision were calculated as CV%.

Results: Baseline characteristics (mean ± SD) were similar between groups in term of age, 69.2 ± 4.4 years; BMI, 23.8±4.4 kg/m2; L1-L4 T-score, -2.9±0.9 and TBS 1.230 ± 0.09. As expected, the correlation between Spine BMD and TBS was very low with r2 = 0.12. Precision errors were 1.1% and 1.6% for spine BMD and TBS, respectively. Over 1 and 2 years, L1-L4 BMD increased significantly by 5.6% and 9% in SrRan group and by 5.2% and 7.6%, respectively in ALN group. Similarly, spine TBS increased by 2.3% (p < 0.001) and 3.1% (p < 0.001) in SrRan group and by 0.5% (ns) and 1.0% (ns) respectively in ALN group with a significant between-group difference in favor of SrRan (p = 0.04 and p = 0.03). There were no correlation between delta BMD and TBS at 1 year or at 2 years. The two treatments were well tolerated. 

Conclusion(s): SrRan has greater effects on bone architecture index at the spine compared to alendronate in women with postmenopausal osteoporosis after 2-year treatment. These results consolidate previous studies supporting a benefit of SrRan on bone architecture.

References: 1. Hans D. et al. J Bone Miner Res 2011;26:2762. 

2. Felsenberg D. et al. Osteoporos Int 2011;22(suppl. 1):S102.

https://sci-hub.se/https://doi.org/10.1007/s00198-012-1928-7

Tuesday, August 23, 2022

Trabecular Bone Score (TBS)

I will be asking that a Trabecular Bone Score (TBS) be included with my next DXA scan. The doctor who read my latest scan wrote, "Follow up with DEXA and TBS: As needed." 

I found a review of TBS. The review includes a section on "Changes in TBS with Treatment of Osteoporosis." Below is the paragraph comparing the effects of strontium ranelate and alendronate (Fosamax) on TBS. 

"The effects of strontium ranelate (SrRan) and alendronate on TBS were evaluated in a post hoc analysis performed in 79 women with postmenopausal osteoporosis of 189 included in a double‐blind, double‐dummy, randomized study. Women were randomized to either SrRan 2 g/day or alendronate 70 mg/week for 2 years. TBS and BMD parameters were assessed in the LS after 12 and 24 months of treatment. Over 1 and 2 years, LS BMD increased significantly by 5.6% and 9.0% in the SrRan group and by 5.2% and 7.6%, respectively, in the alendronate group. LS TBS increased by 2.3% (p < 0.001) and 3.1% (p < 0.001) in the SrRan group, but the change in the alendronate group was not significant (0.5% and 1.0%, respectively). There was a significant between‐group difference with SrRan showing larger TBS increases than alendronate."

Let me reiterate: Over one and two years, Lumbar Spine (LS) BMD increased in both the SrRan (5.6%, 9.0%) and alendronate groups (5.2%, 7.6%). You will note that the SrRan BMD numbers are higher, especially after the second year, than the alendronate numbers. The results are as expected because strontium results in an overestimation of BMD.  

HERE IS THE KICKER: LS TBS increased by 2.3% and 3.1% in the SrRan group, but the change in the alendronate group was not significant (0.5% and 1.0%, respectively). There was a significant between‐group difference with SrRan showing larger TBS increases than alendronate.

Keep in mind that TBS is related to bone microarchitecture and provides skeletal information that is not captured from the standard BMD measurement. TBS may be a better predictor of fracture risk than BMD alone. 
https://www.panoramaortho.com/wp-content/uploads/2019/03/TBS-Rev...


Sunday, August 21, 2022

DXA Scan of 18 August 2022 Showing Normal Density

Below is my recent axial DXA performed on a Horizon Prologic Wi DXA scanner and showing NORMAL BONE DENSITY! Even if my scores are lower by half due to strontium use, the changes are phenomenal. Fifteen years ago, I was diagnosed with osteoporosis. My scans have gotten progressively better since I began taking strontium citrate 14 years ago. For my next DXA scan, I will ask that a Trebecular Bone Score (TBS) be included.Trabecular bone score (TBS) uses standard lumbar spine DXA imaging to assess bone texture inhomogeneity (that is, the number of filled versus unfilled voxels) in order to gauge bone quality and fracture risk. Strontium will not affect TBS as it does DXA. 


EXAM:  DXA AXIAL 8/18/2022

 INDICATION:  Postmenopausal.

 COMPARISON: 1/8/2018


FINDINGS:


Spine:  Total BMD of the spine L1-4 is 1.030 g/cm2, with a T-score of -0.2 and a Z-score of 2.2.


Left Femoral Neck: BMD is 0.741 g/cm2, with a T-score of -1.0  and a Z-score of 1.1.


Left Total Hip: BMD is 0.856 g/cm2, with a T-score of -0.7 and a Z-score of 1.0.


Right Femoral Neck: BMD is 0.752 g/cm2, with a T-score of -0.9 and a Z-score of 1.2.


Right Total Hip: BMD is 0.907 g/cm2, with a T-score of -0.3 and a Z-score of 1.5.


Spine density increased 5.2%. Left hip density decreased 1%. Right hip density increased 0.9%. These percent change findings may be inaccurate as exam was performed with different technique.


FRAX evaluation calculates 10-year probability of fracture:

 Major Osteoporotic: 7.9%%

 Hip: 1.3%%


IMPRESSION:

 Based on BMD, diagnosis is consistent with normal density.

 Follow up with DEXA and TBS: As needed.


WHO CRITERIA FOR T-SCORES:

 < or = -2.5 = osteoporosis

 < -1.0 and -2.5 = osteopenia

 > or = -1.0 = normal density

Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

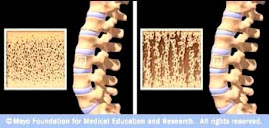
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.