Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Showing posts with label fracture risk assessment tool (FRAX). Show all posts

Sunday, August 21, 2022

DXA Scan of 18 August 2022 Showing Normal Density

Below is my recent axial DXA performed on a Horizon Prologic Wi DXA scanner and showing NORMAL BONE DENSITY! Even if my scores are lower by half due to strontium use, the changes are phenomenal. Fifteen years ago, I was diagnosed with osteoporosis. My scans have gotten progressively better since I began taking strontium citrate 14 years ago. For my next DXA scan, I will ask that a Trebecular Bone Score (TBS) be included.Trabecular bone score (TBS) uses standard lumbar spine DXA imaging to assess bone texture inhomogeneity (that is, the number of filled versus unfilled voxels) in order to gauge bone quality and fracture risk. Strontium will not affect TBS as it does DXA. 


EXAM:  DXA AXIAL 8/18/2022

 INDICATION:  Postmenopausal.

 COMPARISON: 1/8/2018


FINDINGS:


Spine:  Total BMD of the spine L1-4 is 1.030 g/cm2, with a T-score of -0.2 and a Z-score of 2.2.


Left Femoral Neck: BMD is 0.741 g/cm2, with a T-score of -1.0  and a Z-score of 1.1.


Left Total Hip: BMD is 0.856 g/cm2, with a T-score of -0.7 and a Z-score of 1.0.


Right Femoral Neck: BMD is 0.752 g/cm2, with a T-score of -0.9 and a Z-score of 1.2.


Right Total Hip: BMD is 0.907 g/cm2, with a T-score of -0.3 and a Z-score of 1.5.


Spine density increased 5.2%. Left hip density decreased 1%. Right hip density increased 0.9%. These percent change findings may be inaccurate as exam was performed with different technique.


FRAX evaluation calculates 10-year probability of fracture:

 Major Osteoporotic: 7.9%%

 Hip: 1.3%%


IMPRESSION:

 Based on BMD, diagnosis is consistent with normal density.

 Follow up with DEXA and TBS: As needed.


WHO CRITERIA FOR T-SCORES:

 < or = -2.5 = osteoporosis

 < -1.0 and -2.5 = osteopenia

 > or = -1.0 = normal density

Wednesday, May 6, 2015

FRAX Modified by TBS


FRAX®, launched by the WHO Collaborating Centre for Metabolic Bone Diseases in 2008, calculates the10-year probability of osteoporotic fracture based on clinical risk factors, including bone mineral density (BMD) as an optional input.

A new feature of the online FRAX risk assessment tool was launched in April 2014. The output of FRAX can now be adjusted for Trabecular Bone Score (TBS™). Calculated by TBS iNsight™ software which installs on existing DXA scanners, TBS is a simple method that estimates fracture risk based on a determination of bone texture (an index correlated to bone microarchitecture). The predictive ability of TBS is independent of FRAX clinical risk factors and femoral neck bone mineral density (BMD) values. Educational information and scientific publications about TBS are available at www.medimapsgroup.com.

By adding the patient’s TBS value after the FRAX calculation, users will get a 10-year probability of risk of hip fracture and major osteoporotic fracture adjusted for TBS. Clinical advantages of using TBS-adjusted FRAX scores include:
  • Increased accuracy of fracture prediction in the individual
  • Reclassification of  patients’ risk for future fracture above or below an intervention threshold
Following the calculation of FRAX probabilities (at www.shef.ac.uk/FRAX) the TBS value can be manually input by clicking on the TBS button below the calculation results box. Entry of the TBS value, automatically calculated by TBS iNsight™ V.3.0, if installed on your densitometer, produces a ‘FRAX Adjusted for TBS’ score.”

Friday, December 12, 2014

FRAX Accurately Identifies Women at Risk for Vertebral Fracture


By Will Boggs MD
December 01, 2014
  

NEW YORK (Reuters Health) - The WHO fracture risk assessment tool FRAX is better than lumbar spine and femoral neck T-scores at identifying women with vertebral fractures, researchers from Morocco report.

"An elevated FRAX score may be used as a screening tool to indicate bone mineral density (BMD) measurement and vertebral fracture assessment (VFA) at the same time," Dr. Abdellah El Maghraoui from Military Hospital Mohammed in Rabat, Morocco, told Reuters Health. "The cut-off of what is an elevated FRAX has to be determined in different populations."

"Vertebral fractures (VFs) are the most common type of osteoporotic fractures in older adults," Dr. Maghraoui explained. "It has been shown that VFs are usually asymptomatic (only one-fourth to one-third of these fractures come to medical attention). The identification of asymptomatic VFs is of primordial importance especially in patients without densitometric osteoporosis, a common situation where all experts agree to recommend treatment."

Dr. Maghraoui's team developed a Moroccan model based on FRAX and evaluated the performance of FRAX scores in comparison with BMD measurement in identifying women with prevalent asymptomatic vertebral fractures.

Their cross-sectional study included 908 menopausal women aged 50 years and older. Of these women, nearly a third had osteoporosis and 44% had osteopenia.

Vertebral fractures were present in 382 (42.1%) of women, the researchers report in BMC Musculoskeletal Disorders, online November 4.

FRAX without BMD provided the best method of predicting vertebral fracture in these women, and there was no improvement when BMD was added to the model.

A FRAX cutoff of 3%, for example, yielded 57% sensitivity, 78% specificity, 40% positive predictive value, and 2.68 positive likelihood ratio for predicting major fractures.

"The FRAX tool is not designed to examine the risk of asymptomatic vertebral fractions," the researchers say. "However, we performed this analysis because of the importance of this kind of fracture in the outcome of osteoporosis."

"A woman with elevated FRAX should be evaluated further: DXA with VFA, biological exams including vitamin D, iPTH, etc., and in some cases bone turnover markers," Dr. Maghraoui said. "Other factors not included in FRAX should be evaluated such as the risk of fall."

"VFA can easily be performed at the same time of bone mineral density (BMD) measurement, allowing integration of BMD and VF information in the clinical care of patients evaluated for osteoporosis," Dr. Maghraoui concluded. "Advantages of VFA compared with spine radiographs include greater patient convenience (VFA can be done in association with BMD testing by DXA), smaller dose of ionizing radiation, and lower cost."
http://www.medscape.com/viewarticle/835572?src=wnl_edit_tpal&uac=127701PY


For the abstract of this article, see http://strontiumforbones.blogspot.com/2014/12/frax-identifies-women-with-prevalent.html
For the original article, follow either of these two links:

http://bit.ly/1yMo74D
http://www.biomedcentral.com/1471-2474/15/365


Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

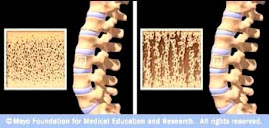
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.