The report of my axial DXA scan taken on 8 January 2019 appears below. I have been on 2 grams strontium citrate/day for 11 years. I also take a calcium/magnesium tablet (500 mg Ca/250 mg Mg), a multivitamin with 1000 IU vitamin D3, and several other supplements. I get plenty of protein in my diet. I exercise daily.
As you can see, my DXA results were excellent, except for my left femoral neck, which showed no change from the previous scan.
I am happy with my results, although I know the comparison of this year's results to those of 2.5 years ago contains some built-in error because two different brands of DXA machines were used. My 2016 scan was on a Hologic and the 2019 scan was on a GE Lunar Prodigy.
Changing testing sites, and, therefore, machines, was not my choice. I had been getting my scans in the outpatient radiology department of a large hospital medical center, but the provider is now pushing patients into its freestanding imaging centers. I was told my insurance would not pay for a DXA unless it was done at a freestanding center, but my insurance denied that assertion.
The risk factor for secondary osteoporosis mentioned, but not specified, in the report is early menopause.
INDICATION: Postmenopausal. Follow-up of osteopenia on prior DXA.
Patient reports risk factors for secondary osteoporosis.
COMPARISON: 8/4/2016
FINDINGS:
Spine: Total BMD of the spine (L1-4) is 1.108 g/cm2, with a T-score of
-0.7 and a Z-score of 1.0.
Left Femoral Neck: BMD is 0.883 g/cm2, with a T-score of -1.1 and a
Z-score of 0.6.
Left Total Hip: BMD is 0.928 g/cm2, with a T-score of -0.6 and a Z-score
of 0.9.
Right Femoral Neck: BMD is 0.919 g/cm2, with a T-score of -0.9 and a
Z-score of 0.9.
Right Total Hip: BMD is 0.963 g/cm2, with a T-score of -0.4 and a Z-score
of 1.1.
Compared to the prior study, there has been 9% increase in spine density, 6% increase in left total hip density, but no change in left femoral neck density.
FRAX evaluation calculates 10-year probability of fracture:
Major Osteoporotic: 7.8%
Hip: 1.0%
IMPRESSION:
Based on BMD, diagnosis is consistent with osteopenia.
FOLLOWUP: In 2 years is recommended.
Human Skeleton

Showing posts with label exercise. Show all posts
Showing posts with label exercise. Show all posts
Friday, January 11, 2019


Friday, July 3, 2015
Treating Sarcopenia
Sarcopenia is, in its most literal
sense, the loss of muscle mass, strength and function related to aging. Most
commonly seen in inactive people, sarcopenia also affects those who remain
physically active throughout their lives. This indicates although a sedentary
lifestyle contributes to this disease, it's not the only factor. In addition,
as we age:
- hormone levels change
- protein requirements alter
- motor neurons die
- and we tend to become more sedentary

These factors in combination are thought
to cause sarcopenia. The figure shows normal muscle mass
on left, muscle wasting on right.
There are currently no approved drug
treatments for sarcopenia. Research is now focusing on the role of physical
activity, nutrition, supplements, and potential future medications that may be
used to treat or prevent sarcopenia.
In a review of literature,
worsening sarcopenia followed trends in losses of muscle strength as well
as impairment of daily functioning. In one study, the prevalence of sarcopenia
increased dramatically with age from 4 % of men and 3 % of women aged 70-75 to
16 % of men and 13 % of women aged 85 or older.
More importantly, when sarcopenia is coupled with other diseases associated with aging, its effects can be even more pronounced. Loss of muscle mass and strength is a significant risk factor for disability in the aging population. When patients suffer from both sarcopenia and osteoporosis, the risk of falling and subsequent fracture incidence is higher. Therefore, treating sarcopenia will in turn help to lessen its burden on co-existing diseases.
Exercise
After
a program of resistance training is introduced, research shows that motor
neuron firing and protein synthesis (both of which are needed in building
muscle mass) increase even in the elderly. These changes indicate it is
possible to rebuild muscle strength even at an advanced age.
Aerobic
exercise also appears to aid in the fight against sarcopenia.
Nutrition
Adequate
nutrition plays a major role in treating sarcopenia. Research has shown
older adults may need more protein per kilogram than their younger counterparts
to maintain proper levels that reinforce muscle mass. Protein
intake of 1.0-1.2 g/kg of body weight per day is probably optimum for older adults.
This theory, coupled with the fact that older adults tend to take in fewer
calories in general, may lead to pronounced protein deficiency as well as
deficiency of other important nutrients. Therefore, maintaining adequate
protein intake as well as adequate caloric intake is an important facet of the
treatment of this disease.
Diets
rich in acid producing foods (meat and cereal grains) and low in non-acid
producing foods (fruits and vegetables) have been shown to have negative
effects on muscle mass. As mentioned above, protein is important,
but a diet high in meat and cereal grains should be balanced with a diet high
in fruits and vegetable (nonacid-producing foods) in order to be effective in
treating sarcopenia.
Supplements
There
is some evidence to support that creatine supplements can also aid in muscle
development for older adults that are following a resistance training program.
Maintaining
appropriate blood levels of vitamin D may also aid in maintaining muscle
strength and physical performance.
Wednesday, March 4, 2015
Exercise Rapidly Improves Bodies and Brains
Identical twins in Finland who
shared the same sports and other physical activities as youngsters but
different exercise habits as adults soon developed quite different bodies and
brains, according to a new study that highlights the extent to which exercise
shapes our health, even in people who have identical genes and nurturing.
The researchers found 10 pairs of young,
male identical twins, one of whom regularly exercised, while the other did not.
The dissimilarities in their exercise routines had mostly begun within the past
three years, according to their questionnaires.
The scientists measured each man’s
endurance capacity, body composition and insulin sensitivity, to determine
their fitness and metabolic health. The scientists also scanned each twin’s
brain.
The sedentary twins had lower
endurance capacities, higher body fat percentages, and signs of insulin
resistance, signaling the onset of metabolic problems. (The twins tended to
have similar diets, so food choices were unlikely to have contributed to health
differences.)
The twins’ brains also were unalike.
The active twins had significantly more gray matter than the sedentary twins,
especially in areas of the brain involved in motor control and coordination.
The researchers concluded the
following:
“Among healthy adult male twins in their mid-30s, a greater
level of physical activity is associated with improved glucose homeostasis and
modulation of striatum and prefrontal cortex gray matter volume, independent of
genetic background. The findings may contribute to later reduced risk of type 2
diabetes and mobility limitations.”
The study was small and not a formal
randomized trial. But the results strongly imply that the differences in the
twin’s exercise habits caused the differences in their bodies.
More subtly, the findings also point
out that genetics and environment do not have to be destiny when it comes to
exercise habits. Even if the input from our DNA and upbringing urges us to skip
the gym, we can move more, and, based on this study, rapidly and substantially
improve the condition of our bodies and brains.
Tuesday, March 31, 2009
Dieters Risk Bone Loss
"What happens to bones during weight loss?" " It depends on how you lose the weight. A study conducted at the Washington University School of Medicine in St. Louis monitored two groups of people who lost a little more than one pound per month for a year. Half of them lost the weight by eating fewer calories, and the other half lost by increasing their physical activity. Despite the gradual rate of weight loss, the dieters lost bone mineral density from their spines and hips. The exercisers lost weight but not bone mass." For more on this subject, see http://archives.starbulletin.com/2008/03/08/features/health.html.
Monday, August 11, 2008
Men And Young Women With Osteoporosis
Mention osteoporosis to most people and they automatically think of women, especially older women, but men and young women can also have brittle bones. According to Dr. Isadore Rosenfeld's article in Parade (May 18, 2008, page 8), two million men is the U.S.A. have the disease, and 12 million more are at risk. I haven't found statistics for young women, but I have read blog posts from several women in their 20's and 30's with osteoporosis.
Causes include:
- Steroids taken to treat asthma or arthritis
- Long-term use of antacids containing aluminum
- Low levels of sex hormones (Hysterectemies in women can cause this.)
- Too much thyroid hormone
- Smoking
- Excessive alcohol consumption
- Lack of exercise
- Inadequate dietary calcium
- Heredity
- Lactation (Nursing mothers lose calcium.)
Subscribe to:
Posts (Atom)
Wandering Skeleton

Artist: Joel Hoekstra
Osteoporotic Bone
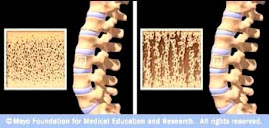
Source: www.mayoclinic.com