WELCOME TO STRONTIUM FOR BONES BLOG
Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.
Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.
Browse the posts and visit the link library of references.
Numerous studies on sr. ranelate
found increasing BMD correlated with decreasing fracture risk (references #16
and #21-25 listed at the end of the Comb Study cited below). The French
pharmaceutical company, Servier, funded the research on sr. ranelate to market
the drug in Europe and elsewhere. Taking a drug through all the required
clinical trials takes millions of dollars and the resources of a large company
like Servier, which is present in 140 countries,
with more than 20,000 employees, including close to 3000 in Research and
Development (R&D).
Strontium
citrate is not patentable and is sold as a supplement in the U.S. and Canada. There
is no monetary incentive for a large pharmaceutical company to do research on
strontium citrate. Any research on sr. citrate is most likely to come from
universities that have obtained grants. We will continue to see small-scale
strontium citrate studies that will add to our knowledge. I do not expect to
see large-scale clinical trials involving thousands of subjects taking
strontium citrate over a period of several years. Those are the types of trials
needed to prove fracture-risk efficacy.
The
following is a review of some significant studies on strontium citrate:
In 2007, two American researchers
with SDM College of Dental Sciences in Buffalo, NY, presented
their work on osteoblasts at a dental conference. They wrote: “The data support the hypothesis that strontium citrate increases
the proliferative/alkaline phosphatase activity of human osteoblastic cells
from alveolar bone. The results validate previous research that has been done
with other forms of strontium in clinical studies and rodent calvarial cells
and indicates that strontium citrate could be a promising agent in treating
oral as well as systemic bone disorders.” The abstract of their paper is available here:
http://iadr.confex.com/iadr/2007orleans/techprogram/abstract_89231.htm
In 2012,
two Canadian researchers, one with the University of Alberta, the other with
the University of Calgary, published the results of a one-year study called the
Combination of Micronutrients for Bone (COMB) Study. The daily protocol consisted
of: docosahexanoic acid or DHA (from Purified Fish
Oil) 250 mg, vitamin D3 2000 IU, vitamin K2 (non-synthetic MK7 form) 100 ug, Strontium
citrate 680 mg elemental strontium, and elemental magnesium 25 mg/day. Dietary
sources of calcium were recommended. Daily impact exercising was encouraged. The
researchers concluded: “This combined micronutrient supplementation regimen appears to
be at least as effective as bisphosphonates or strontium ranelate in raising
BMD levels in hip, spine, and femoral neck sites. No fractures occurred in the
group taking the micronutrient protocol. This micronutrient regimen also
appears to show efficacy in individuals for whom bisphosphonate therapy was
previously unsuccessful in maintaining or raising BMD. Prospective clinical
trials are required to confirm efficacy.” The complete article is available
here: http://www.hindawi.com/journals/jeph/2012/354151/
In July, 2012, four researchers at Ryerson University in
Toronto, Canada, published a study in “Bone” entitled: “Monitoring
bone strontium levels of an osteoporotic subject due to self-administration of
strontium citrate with a novel diagnostic tool, in vivo XRF: a case study.”
This study is significant because it used a non-invasive method (not an
invasive method, such as bone biopsy) to analyze the strontium levels of bones
in an osteoporotic patient who began taking strontium citrate for the study.
Therefore, it was possible to obtain her baseline bone strontium levels prior
to initiation of therapy with strontium citrate. The researchers wrote: “By 120
hours, the increase (in bone strontium level) was statistically significant at
0.68 ± 0.07 and 0.93 ± 0.05 (for the finger and ankle), respectively. Further
increases occurred within an interval of 90-180 days, with the most recent,
after 800 days, at the finger and ankle being 7 and 15 times higher than the
initial baseline reading. The intriguing results show bone strontium
incorporation and retention follow a pattern, suggesting strontium levels, at
least in the ankle, do not plateau within two to three years and will continue
to increase over time, as an individual takes strontium supplements. The ability
of this IVXRF (in vivo X-ray fluorescence) system to monitor and measure bone
strontium levels over time provides a useful diagnostic tool to help gain
insight into strontium bone kinetics.” The abstract can be read here: http://www.ncbi.nlm.nih.gov/pubmed/22549020
The potential
effect of strontium (Sr) on bone apatite (bone mineral) crystals was
investigated in paired biopsies of osteoporotic women treated with either
strontium ranelate (SrRan) or a placebo for 36 months. In ten paired biopsies,
crystallinity, apparent length and width/thickness of crystals, interplanar
distances, and lattice parameters of unit cells were assessed by X-ray
diffraction and selected area electron diffraction. None of these parameters,
reflecting crystal and unit cell characteristics, was influenced by the
presence of Sr. All of the parameters were similar in SrRan and placebo groups
after 36 months of treatment. The mean rate of substitutions of calcium by Sr
ions was 4.5 %. Overall, the quality of bone apatite crystals was maintained
after 36 months of treatment with SrRan. Results of this study were published on
March, 2013, in Osteoporosis
International.
http://www.ncbi.nlm.nih.gov/pubmed/23108780
Researchers have
identified a protein that likely causes osteoporosis in women after menopause. In
experiments on mice, the research team from Tokyo’s Keio University School of
Medicine and other institutions found that a decrease in the secretion of
estrogen enhances the function of HIF1 alpha protein. Once the amount of
estrogen secreted by the ovaries begins to decline around the time of
menopause, HIF1 alpha protein in osteoclasts increases.
Normal mice after
menopause showed decreased femoral bone density compared with premenopausal
levels, but mice whose genes were manipulated so as not to produce the HIF1
alpha protein did not show a decline of femoral bone density even after
menopause. Moreover, a substance to inhibit the function of the HIF1 alpha
protein that was given to postmenopausal mice led to an increase of bone
density compared with premenopausal levels. The discovery is expected to lead
to the development of an effective medicine to prevent osteoporosis.
The study is to
be published in the online edition of the Proceedings of the U.S. National
Academy of Science.
After five and a half years of taking strontium citrate (680
mg strontium daily), I went from osteoporosis to osteopenia. I was probably at
the osteopenia stage much earlier, but I waited four years between my previous
DEXA scan, which showed improvement at all sites but still left me with
osteoporosis, and this one. My density increased 34% in the lumbar spine and
55% in the left hip! These numbers are phenomenal! Even if up to 50% of the
change in BMD were attributed to the effect of strontium, which has a higher
atomic number than calcium and will affect DEXA measurements, the numbers would
still be great. My BMD is now 0.871 g/cm2 at the spine from L1- L4 (T-score -1.6),
0.692 g/cm2 at the left femoral neck (-1.4 T-score), and 0.775 g/cm2 at the
left total hip (-1.4 T-score). Osteopenia is defined as T-scores < -1.0 and
-2.5.
Many of you have probably read that
the only way to measure the amount of strontium in bone is to do a bone biopsy.
That is no longer true, at least not in a research setting. A case study
published last year in Bone used an in vivo X-ray
fluorescence (IVXRF) I-125 based system to measure bone strontium levels
non-invasively in an osteoporotic female volunteer before and after she began
taking strontium citrate supplements (680 mg Sr/day).
Thirty-minute
measurements were taken at the finger and ankle bone sites, representing
primarily cortical and trabecular bone, respectively. Baseline natural strontium levels were obtained followed by a 24h measurement of first
intake of strontium citrate supplements (680 mg Sr/day). The baseline levels of
strontium (prior to supplementation) were 0.38 ± 0.05 and 0.39 ± 0.10 for the
finger and ankle, respectively. After 24 hrs the levels were 0.62 ± 0.14 and
0.45 ± 0.12 for the finger and ankle, respectively. By 120 h, the increase was
statistically significant at 0.68 ± 0.07 and 0.93 ± 0.05, respectively. Further
increases occurred within an interval of 90-180 days, with the most recent,
after 800 days, at the finger and ankle being 7 and 15 times higher than the
initial baseline reading.
The results
show bone strontium incorporation and retention follow a pattern and suggest strontium levels, at least in the ankle, do not plateau within two to
three years and will continue to increase over time, as an individual takes strontium supplements. The ability of this IVXRF system to monitor
and measure bone strontium levels over time provides a useful diagnostic tool to help
gain insight into strontium bone kinetics.
Age and bone
quality are the two most important factors influencing the fracture healing
process. Cellular and molecular alterations in elderly patients may lead to pseudarthrosis
(nonunion), i.e., a fracture that has not united in the stipulated time in
which such fractures usually unite and has no chance of union without
intervention. In the same way, in altered bone metabolism conditions, such as
osteoporosis, physiological phases of fracture healing are impaired.
Two women with
fractures that would not heal were started on strontium ranelate (2g/day),
calcium (1200 mg/day), and vitamin D (800 IU/day). Patient B.G. was a
57-year-old Caucasian woman with osteopenia and a fracture of the right distal
radius and ulna. Patient S.L. was a 59-year-old Caucasian woman with
osteoporosis and a fracture of the base of the fifth metatarsal in the left
foot. Their case studies showed healing of fractures in a short period of time
after drug and supplement intervention.
How Strontium Builds Bones
Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.
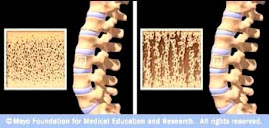
Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.
Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.
When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.