Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Showing posts with label micronutrients. Show all posts

Tuesday, February 14, 2017

MOTS and COMB Study Comparison


A one-year study on strontium citrate combined with melatonin and other supplements and named the Melatonin-micronutrients Osteopenia Treatment Study (MOTS) was recently published (January 26, 2017). I’d like to compare it to the Combination of Micronutrients for Bone (COMB) Study published in 2012. See the following chart:
        
    COMB Study                                                               MOTS

Study size                        114                                                                                  20
Baseline BMD status      osteoporosis                                                                   osteopenia
Strontium (citrate)               680 mg                                                                          450 mg
Vitamin K2 (MK7)               100 mcg                                                                         60 mcg
Melatonin                              none                                                                                5 mg                        
Vitamin D3                         2000 IU                                                                          2000 IU
Docosahexanoic acid (DHA)   250 mg                                                                      none
Magnesium                             25 mg                                                                          none
Lumbar spine BMD             6% increase                                                             4.3% increase
Femoral neck BMD             4% increase                                                             2.2% increase
Total hip BMD               3% increase                                                             No sign. diff., pos. trend

I could have predicted the results on BMD. How? Well, it had previously been shown, from studies on strontium ranelate, that strontium increased BMD at all dosages studied, but the optimum increases were gained with 680 mg strontium. Also, melatonin has been used for years as a sleep aid, but there is little evidence for it as a bone supplement. The authors of MOTS named two studies on melatonin listed below.         

“Limitations to this study include low number of subjects, lack of a diverse cohort and lack of different micronutrient combinations on primary and secondary endpoints in MOTS clinical trial.”

Despite the limitations of MOTS, there is valuable information to be gained from it:

MOTS increased awareness of the importance of preventative care in patients with osteopenia. “Over half of all women in the U.S. above age 50 have osteopenia with a prevalence of approximately 3.4 times more than osteoporosis. Consequently, twice the number of fractures arises from women with osteopenia as they represent almost 50% of the total population at risk.”

“The 10-year vertebral fracture risk probability decreased by 6.48% in response to MSDK (melatonin, strontium, vitamins D and K) therapy compared to 10.8% increase in placebo.”

“MSDK reduced bone marker turnover primarily by increasing the bone formation marker P1NP and maintaining healthy bone turnover.”

“MSDK demonstrated positive effects on inflammatory status and improved quality of life especially related to sleep.”

MOTS confirmed that dosages lower than 680 mg strontium will increase BMD by lower percentages.


Kotlarczyk MP, Lassila HC, O’Neil CK, D’Amico F, Enderby LT, Witt‐Enderby PA, Balk JL. Melatonin osteoporosis prevention study (MOPS): a randomized, double‐blind, placebo‐controlled study examining the effects of melatonin on bone health and quality of life in perimenopausal women. J Pineal Res. 2012; 52:414–26. doi: 10.1111/j.1600‐079X.2011.00956.x

Amstrup AK, Sikjaer T, Heickendorff L, Mosekilde L, Rejnmark L. Melatonin improves bone mineral density at the femoral neck in postmenopausal women with osteopenia: a randomized controlled trial. J Pineal Res. 2015; 59:221–29. doi:10.1111/jpi.12252

Wednesday, December 17, 2014

Strontium Citrate and Strontium Ranelate


Strontium ranelate is prescribed for postmenopausal osteoporosis in the United Kingdom, Australia, much of Europe and Asia, and Mexico. Due to an increased risk of thrombosis and cardiovascular events in patients with a history of cardiovascular problems, some doctors are discouraging their patients from taking strontium ranelate or refusing to prescribe it.

Strontium ranelate is not available in the United States or Canada. However, strontium citrate can be purchased as a supplement from health food stores and online distributors. Is strontium citrate safe and effective?

In 2012, Canadian researchers published the Combination of Micronutrients for Bone (COMB) Study. Here is the abstract:

“Along with other investigations, patients presenting to an environmental health clinic with various chronic conditions were assessed for bone health status. Individuals with compromised bone strength were educated about skeletal health issues and provided with therapeutic options for potential amelioration of their bone health. Patients who declined pharmacotherapy or who previously experienced failure of drug treatment were offered other options including supplemental micronutrients identified in the medical literature as sometimes having a positive impact on bone mineral density (BMD). After 12 months of consecutive supplemental micronutrient therapy with a combination that included vitamin D3, vitamin K2, strontium, magnesium and docosahexaenoic acid (DHA), repeat bone densitometry was performed. The results were analyzed in a group of compliant patients and demonstrate improved BMD in patients classified with normal, osteopenic and osteoporotic bone density. According to the results, this combined micronutrient supplementation regimen appears to be at least as effective as bisphosphonates or strontium ranelate in raising BMD levels in hip, spine, and femoral neck sites. No fractures occurred in the group taking the micronutrient protocol. This micronutrient regimen also appears to show efficacy in individuals where bisphosphonate therapy was previously unsuccessful in maintaining or raising BMD. Prospective clinical trials are required to confirm efficacy.”

Here is the COMB protocol for bone health:
(1) Docosahexaenoic acid or DHA (from Purified Fish Oil): 250 mg/day          
(2) Vitamin D3: 2000 IU/day         
(3) Vitamin K2 (non-synthetic MK7 form): 100 ug/day        
(4) Strontium citrate: 680 mg/day (strontium)       
(5) Elemental magnesium: 25 mg/day      
(6) Dietary sources of calcium recommended        
(7) Daily impact exercising encouraged    

The following two paragraphs are quotes from the paper:
“Studies to date have predominantly focused on strontium ranelate rather than the readily available strontium citrate supplement as used in this study. The results of this study, however, demonstrate that the micronutrient combination including strontium citrate is at least as effective in BMD change as strontium ranelate with suggestion of preferred efficacy of the former therapy at improving femoral neck outcomes. Furthermore, the ranelic acid salt is a purely synthetic molecular compound, while citrate is naturally occurring. It appears to be the strontium portion of the molecules which exerts most or all of the positive effect on bone. When consuming the strontium ranelate, for example, the compound splits into two strontium ions and one molecule of ranelic acid, with each absorbed separately. There is little evidence that the ranelic acid portion of the strontium ranelate compound contributes to the effect of strontium on skeletal tissue, and of the small amount of ranelic acid that is absorbed into the body, almost all is excreted within a week without ever being metabolized. All forms of strontium have bioavailabilities in the 25–30% range, but gastric tolerance appears to be better with the ranelate and citrate forms.”

“With the mounting concern about the safety profile of some standard medical interventions for bone compromise, strontium is very well tolerated and has shown remarkably little in the way of side effects or long-term adverse sequelae. An increased risk of thrombosis has been noted with strontium ranelate, an effect not reported (to our knowledge) with strontium citrate [16].”

16. S. J. Genuis and G. K. Schwalfenberg, “Picking a bone with contemporary osteoporosis management: nutrient strategies to enhance skeletal integrity,” Clinical Nutrition, vol. 26, no. 2, pp. 193–207, 2007.
The abstract to reference 16:
 http://www.clinicalnutritionjournal.com/article/S0261-5614%2806%2900151-8/abstract
The entire article (reference 16) in PDF form:
 http://www.uio.no/studier/emner/medisin/nutri/ERN3120/v12/ERN3120-Unit3-Student/02%20Osteoporosis%20and%20Ostaomalacia/Osteoporose-ern%C3%A6ring-03.pdf

The entire COMB Study article can be read here:


Thursday, February 9, 2012

Combination of Micronutrients for Bone (COMB) Study

After 12 months of consecutive supplemental micronutrient therapy,repeat bone densitometry was performed. The results were analyzed in a group of compliant patients and demonstrate improved BMD in patients classified with normal, osteopenic and osteoporotic bone density.

Combination of Micronutrients (COMB) Protocol for Bone Health

1. Docosahexanoic acid or DHA (from Purified Fish Oil): 250 mg/day
2. Vitamin D3: 2000 IU/day
3. Vitamin K2 (non-synthetic MK7 form): 100 ug/day
4. Strontium citrate: 680 mg/day
5. Elemental magnesium: 25 mg/day
6. Dietary sources of calcium recommended
7. Daily impact exercising encouraged

After one year of therapy with the COMB protocol compared to published results for strontium ranelate and bisphosphonate medications, the percent changes in bone mineral density (z values) were as follows:

Femoral neck: 4% increase for the group on the COMB protocol vs. 2% for strontium ranelate, alendronate, and risedronate

Total hip: 3% increase for the COMB protocol vs. 3-4% for strontium ranelate, 2% for alendronate, and not calculated for risedronate

Total spine: 6% increase for COMB protocol vs. 5-6% for strontium ranelate, 4% for both alendronate and risedronate

This combined micronutrient supplementation regimen appears to be at least as effective as bisphosphonates or strontium ranelate in raising BMD levels in hip, spine, and femoral neck sites. No fractures occurred in the group taking the micronutrient protocol. This micronutrient regimen also appears to show efficacy in individuals for whom bisphosphonate therapy was previously unsuccessful in maintaining or raising BMD. Prospective clinical trials are required to confirm efficacy.

This study by Stephen J. Genuis and Thomas P. Bouchard was published in the Journal of Environmental and Public Health, Volume 2012 (2012), Article ID 354151,doi:10.1155/2012/354151 COMB Protocol

Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

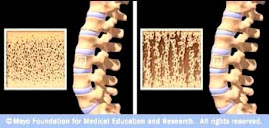
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.