Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Monday, January 26, 2015

Adverse Skeletal Effects of Drugs


There is an expanding list of drugs for which there are concerns regarding adverse skeletal effects. The effect of long-term use of glucocorticoid drugs to cause accelerated bone loss and increase the risk of fracture is well recognized. For some drugs (TKIs, calcineurin inhibitors and loop diuretics), the available data are inconsistent and/or do not support a definite adverse skeletal effect. Patients receiving these drugs can be managed in line with guidelines for the general population (See table). Other drugs (SSRIs, antipsychotic drugs, AEDs and PPIs) do not seem to affect bone metabolism or BMD, but there is evidence for increased fracture risk. However, the evidence is limited to observational data, and any relationship may be attributable either to nonbone effects of the drug or effects of the underlying condition to increase fracture rate. In these patients, evaluation for other risk factors for fracture and management of these risk factors should be considered. In a third group (depot MPA, chemotherapy and ART), there is evidence for increased bone loss and/or fracture, but the patient population is generally at low risk for fracture. In these cases, patients may require an assessment of risk, but will rarely require specific treatment for fracture risk reduction. In the last group (aromatase inhibitors, GnRH agonists and thiazolidinediones), there is evidence of increased risk of bone loss and/or fracture, and the drugs are more frequently prescribed to individuals at higher baseline fracture risk. Patients receiving these drugs require risk assessment and those at high risk of fracture should receive alternative treatments (or "add-back" HRT in the case of GnRH agonists) or, if necessary, specific treatment for osteoporosis.


Table:  Summary of management recommendations
Example drugs
Evidence for risk
Management recommendations
Tyrosine kinase inhibitors

   Calcineurin inhibitors

   Loop diuretics
No adverse 
skeletal effect 
or data 
inconsistent
Manage as per general population


Selective serotonin re-uptake inhibitors (SSRIs)

   Antipsychotics

   Anti-epileptic drugs

   Proton pump inhibitors
Evidence for increased fracture risk but fracture risk seems to relate to nonbone effects of the drug or effects of the underlying condition
Evaluate for other risk factors for fracture and manage these risk factors


Depot medroxyprogesterone acetate

   Chemotherapy

   Antiretroviral therapy
Evidence for increased bone
loss and/or 
fracture, but low
risk population
Assessment of fracture risk, but will rarely require specific treatment


Aromatase inhibitors

   Gonadotrophin hormone-releasing hormone agonists

   Thiazolidinediones


Evidence for increased risk of bone loss and/or fracture, and the drugs are more frequently prescribed to individuals at higher baseline fracture risk

Assessment of fracture risk and those at high risk should receive alternative treatments and/or specific treatment for osteoporosis.


 The conclusions and table are from a longer article, “Adverse Skeletal Effects of Drugs – Beyond Glucocorticoids,” by Susannah O'Sullivan and Andrew Grey, Clin Endocrinol. 2015;82(1):12-22. 


Sunday, January 25, 2015

My DXA Scan Results Look Great After Strontium Citrate


My first DXA scan was in May, 2007 (diagnosed with osteoporosis):

Spine from L1-L4 T-score -3.0
Left hip (total) T-score -2.2
Left femoral neck T-score -2.8

My second DXA scan was in July, 2009 (After 6 months on Fosamax once weekly and 18 months on strontium citrate, 680 mg strontium daily, still at osteoporosis, but scores improved):

Spine (total) T-score -2.7
Left hip (total) T-score -1.7
Left hip (neck) T-score -2.6

My third DXA scan was in August, 2013 (After 5 ½ years on strontium citrate, scan results were at the osteopenia stage; I was probably at the osteopenia stage before this, but I did not have a DXA scan in 2011):

Spine from L1-L4 T-score -1.6
Left hip (total) T-score -1.4
Left hip (neck) T-score -1.4

Osteopenia is defined as T-scores < -1.0 and -2.5.

Thursday, January 22, 2015

Strontium Minerals Come from Mexico


Strontium (Sr) occurs in nature as mineral deposits of celestine (celestite) (strontium sulfate) and strontianite (strontium carbonate). Citric acid and citrate also occur in nature. The chelate strontium citrate (as provided in supplemental form) is made synthetically from strontium minerals and citrate.

Celestite is the most commonly used strontium mineral. The strontium compounds in the government report referenced below are strontium oxide, sr. hydroxide, sr. peroxide, sr. nitrate, and sr. carbonate.  

Import Sources (2009–12): Strontium minerals: Mexico, 100%. Strontium compounds: Mexico, 80%; Germany, 12%; China, 7%; and other, 1%. Total imports: Mexico, 87%; Germany, 8%; China, 4%; and other, 1%.

One hundred percent (100 %) of the strontium minerals imported into the U.S. come from Mexico. None of the strontium minerals imported into the U.S. come from China.

Some time ago, I wrote to Doctor’s Best and asked if its Strontium Bone Maker, a product I take, comes from China. A representative from the company said, “No, our product is U.S.-made.”  Well, that answer was true to a point. Doctor’s Best probably buys strontium citrate from another company that imports celestite from Mexico to make strontium citrate in the U.S. I had to do a lot of sleuthing on the internet to find this information.

I keep hearing from people concerned that the strontium they take, or are considering taking, comes from China. I’ve also read posts on osteoporosis forums from so-called “experts” who keep repeating false information about strontium coming from China. For these reasons, I decided to post this information, citing a U.S. government publication for import sources.

It would be possible for a company to import strontium compounds (sr. carbonate, sr. nitrate) manufactured in China and then make sr. citrate from those, but it is unlikely when the mineral, celestite (strontium sulfate), is available from Mexico. A mine in China is believed to be the only developed strontianite deposit in the world per Hong, Wei, 1993, Celestite & strontianite—Review of ore processing and exploration: Industrial Minerals, no. 309, June, p. 55, as cited in “Strontium” by Joyce A. Ober.


As already stated, the U.S. is not importing strontium minerals from China.
Other than the natural occurrence as mineral, strontium carbonate is prepared synthetically in one of two manners. First of which is from naturally occurring celestine also known as strontium sulfate (SrSO4) or by using soluble strontium salts by the reaction in solution with a soluble carbonate salt (usually sodium or ammonium carbonates). For example if sodium carbonate was used in solution with strontium nitrate:

Sr(NO3)2 (aq) + Na2CO3 (aq) → SrCO3 (s) + 2 NaNO3 (aq).


Since 100% of the strontium minerals imported into the U.S. come from Mexico, and only 7% of the strontium compounds come from China, there is only a small chance the strontium in your strontium citrate supplement came from China.


Alternatives to Citrate Products—Strontium and Calcium and Magnesium


Some people get an upset stomach when taking citrate supplements, such as calcium or magnesium or strontium citrate. A citrate is a derivative of citric acid. What are these people to do?

One possible substitute for strontium citrate is strontium carbonate. Health Concerns BioStrong tablets contain 750 mg of strontium carbonate (340 mg active) and BioPerine (Black Pepper Fruit extract). The manufacturer suggests two tablets per day between meals. This product is available at www.amazon.com. Strontium carbonate is not as well absorbed as sr. citrate. The BioPerine is supposed to help absorption; so, this may be a good formula, but I have not tried it. It has a 5-star rating and 5 reviews at Amazon.

When it comes to calcium supplements, there are many choices beside ca. citrate. Other choices include   calcium alpha-ketogutarate, ca. ascorbate, ca. aspartate, ca. carbonate, ca. gluconate, ca. hydroxyapatite, ca. lysinate, ca. malate, ca. pyruvate. Some calcium supplements combine calcium from several calcium salts. Coral calcium is a calcium salt derived from fossilized coral reefs (primarily from limestone and coastal deposits). Coral calcium is composed primarily of calcium carbonate, with small amounts of magnesium and other trace minerals. Oyster shell calcium is calcium carbonate from oyster shells.

I use Country Life, Gluten Free, Calcium-Magnesium Complex tablets. One serving (two tablets) contains 1000 mg calcium (as calcium hydroxyapatite, citrate, aspartate, alpha-ketoglutarate, lysinate), 500 mg phosphorus (as calcium hydroxyapatite), and 500 mg magnesium (as magnesium oxide, citrate, aspartate, taurinate, alpha-ketoglutarate). I take only one tablet (1/2 serving) per day. The rest of my calcium comes from food plus 162 mg (as calcium carbonate) in my multivitamin. This formulation does contain calcium citrate and magnesium citrate, but they are combined with several other sources of both minerals. This product has a 4 ½-star rating, 180 reviews for the 180-tablet size and 51 reviews for the 360-tablet size at www.iherb.com, where I buy all my supplements.


Solgar, Chelated Calcium contains 1000 mg calcium (as calcium glycinate amino acid chelate, calcium carbonate) per serving of six tablets that can be taken in two doses or more, preferably with meals. This product has 4 ½-stars at www.iherb.com. I have not tried it.

There are several sources of magnesium besides magnesium citrate. As noted above, I get my magnesium from Country Life, Gluten Free, Calcium-Magnesium Complex. The magnesium in this product is from five sources: magnesium oxide, citrate, aspartate, taurinate, and alpha-ketoglutarate. Other sources of magnesium include magnesium chloride, glycinate chelate, malate, and oxide. 

One tablet of Now Foods, Magnesium Malate, 1000 mg contains 150 mg magnesium (from 1000 mg magnesium malate) and 100 mg calcium (from calcium carbonate).  As a dietary supplement, take one tablet 3 times daily, preferably with meals, for a total of 450 mg magnesium and 300 mg calcium. This product has a 4 1/2-star rating and 57 reviews at www.iherb.com. I have never tried these tablets.

Bluebonnet Nutrition, Chelated Magnesium has 200 mg magnesium (as magnesium glycinate chelate, magnesium oxide) in one capsule. It has a 4 1/2-star rating and 66 reviews at www.iherb.com. I have not used this product.


Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

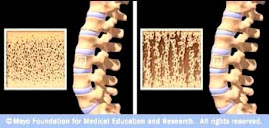
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.