Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Monday, December 15, 2014

Fixed Risk Factors for Osteoporosis


Fixed risk factors determine whether an individual is at heightened risk of osteoporosis. Also, unlike modifiable risks, they are factors which we can’t change, including age, gender and family history.
In addition, people may have secondary risk factors. These include disorders and medications that weaken bone and affect balance (heightening the risk of fracture due to falling). Read more about Secondary Osteoporosis.

Low bone mineral density, one of the most important indicators that a person is at risk of a fracture, is considered both fixed and modifiable since it is determined by a wide range of factors, including family history, age and lifestyle factors.

Although fixed risk factors for osteoporosis cannot be changed, people need to be aware of these risks so that they can take steps to reduce bone mineral loss as early as possible. These risks include:
Age
The majority of hip fractures (90%) occur in people aged 50 and older. This is partly due to reduced bone mineral density as we age. But age can also be a risk factor independent of bone mineral density. In other words, even older adults with normal bone mineral density are more likely to suffer a fracture than younger people1.
Female gender
Women, particularly post-menopausal women, are more susceptible to bone loss than men, because their bodies produce less estrogen. This hormone is an important component in bone formation. Women are more likely to sustain an osteoporotic fracture than men. Lifetime risk of any fracture ranges between 40-50% in women, compared to 13-22% in men.
Family history
A parental history of fracture (particularly a family history of hip fracture) is associated with an increased risk of fracture that is independent of bone mineral density2.
Previous fracture
A previous fracture increases the risk of any fracture by 86%, compared with people without a prior fracture. Both men and women are almost twice (1.86 times) as likely to have a second fracture compared to people who are fracture free3.
Ethnicity
Studies have found osteoporosis is more common in Caucasian and Asian populations, and the incidence of osteoporosis and fractures of the hip and spine is lower in black than in white people.
Menopause or hysterectomy
Hysterectomy, if accompanied by removal of the ovaries, may also increase the risk for osteoporosis because of estrogen loss. Post-menopausal women, and those who have had their ovaries removed, must be particularly vigilant about their bone health.
Long term glucocorticoid therapy
Long-term corticosteroids use is a very common cause of secondary osteoporosis and is associated with an increased risk of fracture4.
Rheumatoid arthritis
Rheumatoid arthritis and diseases of the endocrine system can take a heavy toll on bones. Hyperparathyroidism, for example, results in elevated levels of parathyroid hormone, which signals bone cells to release calcium from bone into the blood.
Primary or secondary hypogonadism in men
Like estrogen deficiency in women (which is observed in case of primary or secondary amenorrhea and premature menopause), androgen deficiency in men (primary or secondary hypogonadism) increases the risk of fracture.

At any age, acute hypogonadism, such as that resulting from orchidectomy for prostate cancer, accelerates bone loss to a similar rate as seen in menopausal women. The bone loss following orchidectomy is rapid for several years, and then reverts to the gradual loss that normally occurs with aging.
Secondary Risk Factors
Secondary risk factors are less prevalent but they can have a significant impact on bone health and fracture incidence. These risk factors include other diseases that directly or indirectly affect bone remodeling and conditions that affect mobility and balance, which can contribute to the increased risk of falling and sustaining a fracture.
Disorders that affect the skeleton:
  • Asthma
  • Nutritional/gastrointestinal problems (e.g. Crohn’s or celiac disease)
  • Rheumatoid arthritis
  • Hematological disorders/malignancy
  • Some inherited disorders
  • Hypogonadal states (e.g. Turner syndrome/Kleinfelter syndrome, amenorrhea)
  • Endocrine disorders (e.g. Cushing’s syndrome, hyperparathyroidism, diabetes)
  • Immobility
Medical treatments affecting bone health:

Some medications may have side effects that directly weaken bone or increase the risk of fracture due to fall or trauma. Patients taking any of the following medications should consult with their doctor about increased risk to bone health.
  • Glucocorticosteroids
  • Certain immunosuppressant (calmodulin/calcineurine phosphatase inhibitors)
  • Thyroid hormone treatment (L-Thyroxine)
  • Certain steroid hormones (medroxyprogesterone acetate, leutenising hormone releasing hormone agonists)
  • Aromatase inhibitors
  • Certain antipsychotics
  • Certain anticonvulsants
  • Certain antiepileptic drugs
  • Lithium
  • Methotrexate
  • Antacids
  • Proton pump inhibitors 
References
1. Kanis JA, Johnell O, Odén A, Dawson A, De LAet C, Jonsson B. Ten year probabilities of osteoporotic fractures according to BMD and diagnosis thresholds. Osteoporosis Int 2001; 12:989-95
2. Kanis JA, Johansson H, Odén A, Johnell O, De LAet C, Eisman JA, McCloskey EV, Mellström D, Melton LJ III, Pols HA, Reeve J, Silman AJ, Tenenhouse A. A family history of fracture and fracture risk: a meta-analysis. Bone 2004; 35:1029-37
3. Kanis JA, De LAet C, Delmas P, Garnero P, Johansson H, Johnell O, Kriger H, McCloskey EV, Mellstrom D, Melton LJ III, Odén A, Pols H, Reeve J, Silman A, tenehouse A. A meta-analysis of previous fracture and fracture risk. Bone 2004; 35: 375-82
4. Kanis J A, Johansson H, Odén A, Johnell O, De Laet C, Melton LJ III, Tenenhouse A, Reeve J, Silman AJ, Pols H, Eisman JA, McCliskey EV, Mellström D. A meta-analysis of prior corticosteroid use and fracture risk. J Bone and Miner Res 2004;19: 893-99

Modifiable Risk Factors for Osteoporosis and Fractures


Most modifiable risk factors, which arise primarily because of unhealthy diet or lifestyle choices, directly impact bone biology and result in a decrease in bone mineral density (BMD). Some modifiable risk factors also increase the risk of fracture independently of their effect on bone itself.

The good news is everyone can take steps to reduce these risk factors for osteoporosis and related fractures.
Modifiable risk factors include:
Alcohol
People with excessive alcohol consumption (>2 units daily) have a 40% increased risk of sustaining any osteoporotic fracture, compared to people with moderate or no alcohol intake. High intakes of alcohol cause secondary osteoporosis due to direct adverse effects on bone-forming cells, on the hormone that regulates calcium metabolism and poor nutritional status (calcium, protein and vitamin D deficiency)1.
Smoking
People with a past history of cigarette smoking and people who smoke are at increased risk of any fracture, compared to non-smokers2.
Low Body Mass Index
Leanness (body mass index (BMI) less than 20 kg/m2) regardless of age, sex and weight loss, is associated with greater bone loss and increased risk of fracture. People with a BMI of 20kg/m2 have a two-fold increased risk of fracture compared to people with a BMI of 25 kg/m2
Poor nutrition
When insufficient calcium is absorbed from dietary sources, the body produces more parathyroid hormone, which boosts bone remodeling, mobilizing osteoclasts in the bone to break down and sacrifice bone calcium to supply the nerves and muscles with the mineral they need. There are indications that protein is also important in that it may act synergistically with vitamin D and calcium.
Vitamin D deficiency
Vitamin D is also essential, since it helps calcium absorption from the intestines into the blood. Vitamin D is made in our skin with exposure to the sun’s ultraviolet rays. In most people casual exposure to the sun for as little as 10-to-15 minutes a day is usually sufficient. However in elderly people, people who do not go outdoors, and during the winter months in northern latitudes, food or supplemental sources of vitamin D is of importance. At least 800 international units of vitamin D and 1,000 to 1,200 mg of calcium daily can protect against osteoporosis3.
Eating disorders
Osteoporosis can also be compounded by eating disorders such as anorexia nervosa and bulimia.
Estrogen deficiency
Estrogen deficiency in women afflicted by these disorders speeds up bone loss in a similar way to that which occurs in post-menopausal women, but to make matters worse, these diseases reduce the robust build up of bone mineral density that usually occurs in adolescence and early adulthood. This may be related to both hormone imbalance and nutritional factors.
Insufficient exercise
People with a more sedentary lifestyle are more likely to have a hip fracture than those who are more active. For example, women who sit for more than nine hours a day are 50% more likely to have a hip fracture than those who sit for less than six hours a day. Read more about the role of exercise in bone health.
Frequent falls
Visual impairments, loss of balance, neuromuscular dysfunction, dementia, immobilization, and use of sleeping pills which are quite common conditions in elderly persons, significantly increase the risk of falling and accordingly increase the risk of fracture. Ninety percent of hip fractures result from falls4.

References
  1.  Kanis JA, Johnell O, Odén A, Johansson H, De Laet C, Eisman JA, Fujiwara S, Kroger H, McCloskey, Mellstrom D, Melton LJ III, Pols H, Reeve J, Silman A, Tenehouse A. Smoking and fracture risk: a meta-analysis. Osteoporosis Int. 2005;16:155-62
  2. Kanis JA. Johansso H, Johnell O, Odén A, De Laet C, Eisman J, Pols H, Tenenhouse A. Alcohol intake as a risk factor for fracture. Osteoporosis Int 2005;16:737-42
  3. Dawson-Hughes B, Heaney RP, Holick MF, et al. (2005) Estimates of optimal vitamin D status. Osteoporos Int 16:713-716
  4. Woolf AD, Akesson K. Preventing fractures in elderly people. BMJ 2003; 327:89-95

Friday, December 12, 2014

FRAX Accurately Identifies Women at Risk for Vertebral Fracture


By Will Boggs MD
December 01, 2014
  

NEW YORK (Reuters Health) - The WHO fracture risk assessment tool FRAX is better than lumbar spine and femoral neck T-scores at identifying women with vertebral fractures, researchers from Morocco report.

"An elevated FRAX score may be used as a screening tool to indicate bone mineral density (BMD) measurement and vertebral fracture assessment (VFA) at the same time," Dr. Abdellah El Maghraoui from Military Hospital Mohammed in Rabat, Morocco, told Reuters Health. "The cut-off of what is an elevated FRAX has to be determined in different populations."

"Vertebral fractures (VFs) are the most common type of osteoporotic fractures in older adults," Dr. Maghraoui explained. "It has been shown that VFs are usually asymptomatic (only one-fourth to one-third of these fractures come to medical attention). The identification of asymptomatic VFs is of primordial importance especially in patients without densitometric osteoporosis, a common situation where all experts agree to recommend treatment."

Dr. Maghraoui's team developed a Moroccan model based on FRAX and evaluated the performance of FRAX scores in comparison with BMD measurement in identifying women with prevalent asymptomatic vertebral fractures.

Their cross-sectional study included 908 menopausal women aged 50 years and older. Of these women, nearly a third had osteoporosis and 44% had osteopenia.

Vertebral fractures were present in 382 (42.1%) of women, the researchers report in BMC Musculoskeletal Disorders, online November 4.

FRAX without BMD provided the best method of predicting vertebral fracture in these women, and there was no improvement when BMD was added to the model.

A FRAX cutoff of 3%, for example, yielded 57% sensitivity, 78% specificity, 40% positive predictive value, and 2.68 positive likelihood ratio for predicting major fractures.

"The FRAX tool is not designed to examine the risk of asymptomatic vertebral fractions," the researchers say. "However, we performed this analysis because of the importance of this kind of fracture in the outcome of osteoporosis."

"A woman with elevated FRAX should be evaluated further: DXA with VFA, biological exams including vitamin D, iPTH, etc., and in some cases bone turnover markers," Dr. Maghraoui said. "Other factors not included in FRAX should be evaluated such as the risk of fall."

"VFA can easily be performed at the same time of bone mineral density (BMD) measurement, allowing integration of BMD and VF information in the clinical care of patients evaluated for osteoporosis," Dr. Maghraoui concluded. "Advantages of VFA compared with spine radiographs include greater patient convenience (VFA can be done in association with BMD testing by DXA), smaller dose of ionizing radiation, and lower cost."
http://www.medscape.com/viewarticle/835572?src=wnl_edit_tpal&uac=127701PY


For the abstract of this article, see http://strontiumforbones.blogspot.com/2014/12/frax-identifies-women-with-prevalent.html
For the original article, follow either of these two links:

http://bit.ly/1yMo74D
http://www.biomedcentral.com/1471-2474/15/365


Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

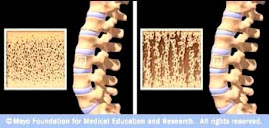
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.