Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Showing posts with label SOTI study. Show all posts

Thursday, August 7, 2014

Effect of Strontium Ranelate on the Risk of Osteoporotic Fractures


Summary
The aim of the present study was to determine the efficacy of strontium ranelate as a function of baseline fracture risk. Treatment with strontium ranelate was associated with a significant 31% decrease in all clinical osteoporotic fractures (vertebral fractures included). Hazard ratios for the effect of strontium ranelate on the fracture outcome did not change significantly with increasing fracture probability.

Introduction
 Two previous studies have suggested that the efficacy of intervention may be greater in the segment of the population at highest fracture risk as assessed by the FRAX® algorithms. The aim of the present study was to determine whether the anti-fracture efficacy of strontium ranelate was dependent of the level of fracture risk.

Methods
The primary data of the two phase III studies (SOTI and TROPOS) of the effects of strontium ranelate in postmenopausal osteoporosis were combined. Country-specific probabilities were computed using the FRAX® tool (version 2.0). The primary outcome variable comprised all clinical osteoporotic fractures (including clinical vertebral fractures). Interactions between fracture probability and efficacy were explored by Poisson regression.

Results
The 10-year probability of major osteoporotic fractures (with BMD) ranged from 2.5% to 90.8%. FRAX®-based hip fracture probabilities ranged from 0.1% to 90.3%. The incidence of clinical osteoporotic fractures (vertebral fractures excluded) and morphometric vertebral fractures increased with increasing baseline fracture probabilities. Treatment with strontium ranelate was associated with a 31% (95% CI = 20–39%) decrease in osteoporotic clinical fractures and a 40% decrease in vertebral fractures assessed by semiquantitative morphometry (95% CI = 31–48%) Hazard ratios for the effect of strontium ranelate on the fracture outcomes did not change significantly with increasing fracture probability.

Conclusion
Strontium ranelate significantly decreased the risk of osteoporotic clinical fractures, non vertebral fractures and morphometric vertebral fractures in women. Overall, the efficacy of strontium ranelate was not dependent of the level of fracture risk assessed by FRAX.

 
http://link.springer.com/article/10.1007/s00198-010-1474-0#page-1

Friday, December 23, 2011

Effects of Strontium Ranelate on Spinal Osteoarthritis Progression

In “Effects of strontium ranelate on spinal osteoarthritis progression,” published in Ann Rheum Dis 2008;67:335-339, O Bruyere et al aimed to determine whether a three-year treatment with strontium ranelate could delay the progression of spinal osteoarthritis (OA). This study was a post-hoc analysis of pooled data from the Spinal Osteoporosis Therapeutic Intervention (SOTI) and TReatment Of Peripheral OSteoporosis (TROPOS) trials performed on 1,105 women with osteoporosis and concomitant radiological spinal OA at baseline, and for whom lumbar x-rays were available at baseline and over the three-year treatment period. The presence and severity of osteophytes, disc space narrowing and sclerosis in the lumbar intervertebral spaces was graded, and an overall OA score was calculated for each intervertebral space. Back pain (measured on a five-point Likert scale only in SOTI) and health-related quality of life (SF-36 questionnaire) were assessed at baseline and after three years. Patients who suffered an incident or progressive vertebral fracture during the study were excluded from the analysis. The proportion of patients with worsening overall spinal OA score was reduced by 42% in the strontium ranelate group, compared with placebo. Significantly more patients in the strontium ranelate group experienced an improvement in back pain after three years, compared with placebo, while no significant difference was observed in terms of health-related quality of life between these patient groups. The researchers concluded that strontium ranelate could reduce the progression of the radiographic features of spinal osteoarthritis (OA) and back pain in women with osteoporosis and prevalent spinal OA. http://ard.bmj.com/content/67/3/335.abstract.

Friday, July 22, 2011

Strontium Ranelate And Risk Of Vertebral Fractures In Frail Osteoporotic Women

Data were obtained from the SOTI (Spinal Osteoporosis Therapeutic Intervention) and TROPOS (Treatment Of Peripheral Osteoporosis) studies which randomized participants to receive either strontium ranelate or placebo over three years. The study identified 2346 robust, 2472 intermediate and 264 frail women. At three years, the risk for vertebral fractures was reduced by 30% in the robust, by 45% in the intermediate, and by 58% in the frail patients compared to those assigned to placebo. Risk of vertebral fracture was reduced within one year in all three groups.
This study was published by Rolland Y, Van Kan GA, Gillette-Guyonnet S, Roux C, Boonen S, and Vellas B in Bone 2011;48:332-8.

Thursday, November 5, 2009

BMD Improvements With Strontium

Research indicates that over three years, strontium can improve bone mineral density by 8-14%, depending on the site. These findings come from three studies on strontium ranelate (STRATOS, SOTI, and TROPOS). One study on strontium malonate (Strong study) showed a 2.66% increase in BMD at the lumbar spine after just three months. The University of California at Davis (UCD) is conducting a three-month clinical trial on strontium citrate, but the results may not be available before May, 2010.

The STRATOS trial (2002) of strontium ranelate determined that 680 mg strontium was the optimum dose. It was followed by a much larger study (SOTI study, 2004) of 1,649 osteoporotic postmenopausal women over a three-year period. Participants that received 680 mg of strontium daily, along with calcium and vitamin D supplements, increased lumbar bone mineral density by an average of 14.4% and femoral neck BMD an average of 8.3%.

The TROPOS study in 2005 focused on non-vertebral fractures in 5,091 postmenopausal women with osteoporosis. After five years, this double-blind, placebo-controlled study found an 8.2% improvement in the femoral neck and a 9.8% improvement in the total hip bone density.

In 2007, Osteologix, Inc. announced the results of its phase II clinical trial (Strong study) involving 289 postmenopausal women with low bone mineral density. The company reported that after three months, a 680 mg dose of strontium malonate increased lumbar spine BMD by 2.66%.

Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

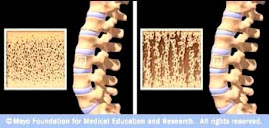
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.