Sara S. DeHart, MSN, Ph.D., is an 80-year-old woman who was diagnosed with osteopenia at age 63. She was treated initially with Fosamax 10 mg. daily and Estraderm patches twice weekly. She discontinued the patches after about two
years, and Fosamax after about three years. Following a fragility fracture of
the sacrum, she was prescribed Actonel 5 mg five times a week. Her vitamin D
blood level was found to be very low, although she had supplemented with 400 IU vitamin D3 throughout her adult life.
She followed “standards of care” medical
recommendations until she developed a second fragility fracture at T9 while
taking Actonel. At that point, she stopped using Actonel and began taking strontium citrate. She increased her vitamin D3
supplementation. Today, she is 80 years old and her BMD is normal. More
importantly, she has not fractured, even after a recent fall onto an asphalt
driveway! Follow this link to read her amazing story:Human Skeleton

Tuesday, October 9, 2012


Sunday, August 19, 2012
Methods for Assessing Bone Quality
Bone mass, geometry, and tissue material
properties contribute to bone structural integrity. Thus, bone strength arises
from both bone quantity and quality. Bone quality encompasses the geometric and
material factors that contribute to fracture resistance. Although no single
method can completely characterize bone quality, current noninvasive imaging
techniques can be combined with ex vivo mechanical and compositional techniques
to provide a comprehensive understanding of bone quality.
Methods for assessing mechanical properties
include whole-bone, bulk tissue, microbeam, and micro- and nanoindentation
testing techniques. Outcomes include structural strength and material modulus.
Advantages include direct assessment of bone strength; disadvantages include
specimen destruction during testing.
Methods for characterizing bone geometry and
microarchitecture include quantitative CT, high-resolution peripheral
quantitative CT, high-resolution MRI, and micro-CT. Outcomes include
three-dimensional whole-bone geometry, trabecular morphology, and tissue
mineral density. The primary advantage is the ability to image noninvasively;
disadvantages include the lack of a direct measure of bone strength.
Methods for measuring tissue composition
include scanning electron microscopy, vibrational spectroscopy, nuclear
magnetic resonance imaging, and chemical and physical analytical techniques.
Outcomes include mineral density and crystallinity, elemental composition, and
collagen crosslink composition. Advantages include the detailed material
characterization; disadvantages include the need for a biopsy.
Clinical
Orthopaedics and Related Research, Volume 469, Number 8 (2011), 2128-2138.
Tuesday, August 14, 2012
Is Strontium Ranelate Safe?
“Clinical
trials are designed to assess efficacy, not safety and so post marketing data
is needed to evaluate safety. Jakob et al report the results
of an observational cohort study to assess safety and treatment persistence
with SR during 3 years follow-up in 12,702 postmenopausal women from 7
countries (29).
Mean age was 69.0 years with 16.5% of patients being over 80 years. Mean
follow-up duration was 32 months and mean treatment duration was 25.2 months
(24,956 patient-years of treatment). VTE was reported in 55 patients, an
incidence of 2.1/1000 patient-years (95% CI 1.6, 2.8), lower than that observed
in patients treated with SR in the phase III studies (7.9/1000 patient-years;
95% CI 6.3, 9.7). No DRESS syndrome or Stevens-Johnson syndrome was reported.
Persistence of SR treatment was 80%, 68% and 64% after 12, 24 and 32 months
treatment, respectively.”
29.
Jakob FJ, Palacios S, Audran M, et al. Final results of a 3 years prospective
observational cohort study of patients treated with strontium ranelate.
Osteoporos Int 2012;23(Suppl 2):S73.
Thursday, July 5, 2012
Vitamins B6 and B12 and Folic Acid
Readers of my blog know that I advocate taking strontium citrate along with a combination of vitamins, minerals, and other supplements for bone health. Most people understand that calcium, magnesium, and vitamin D are essential for strong bones. Some people are adding vitamin K1 and/or vitamin K2 (MK4 or MK7) to their supplement lists. But did you know that you may also need vitamins B6 and B12 and folic acid?
“Some studies suggest high blood levels of the amino acid homocysteine may be linked to lower bone density and higher risk of hip fracture in the elderly. Vitamins B6 and B12, as well as folic acid, play a role in changing homocysteine into other amino acids for use by the body; so, it is possible that they might play a protective role in osteoporosis. Research is ongoing as to whether supplementation with these B vitamins might reduce fracture risk.” This paragraph is quoted from:
http://www.iofbonehealth.org/nutrition
The studies referred to are:
1. McLean RR, Jacques PF, Selhub J, et al. (2004) Homocysteine as a predictive factor for hip fracture in older persons. N Engl J Med 350:2042-49
2. Morris MS, Jacques PF, Selhub J (2005) Relation between homocysteine and B-vitamin status indicators and bone mineral density in older Americans. Bone 37:234-42
I take Nature's Bounty Sublingual Vitamin B12, 5000 mcg (5 mg) per microlozenge. I was using it three times per week, but I have recently increased my intake to the recommended dosage of one microlozenge daily. You dissolve these under your tongue for maximum absorption.
My multivitamin, Nature Made Multi For Her 50+, contains 6 mg of vitamin B6,25 mcg of vitamin B12, and 400 mcg of folic acid.
“Some studies suggest high blood levels of the amino acid homocysteine may be linked to lower bone density and higher risk of hip fracture in the elderly. Vitamins B6 and B12, as well as folic acid, play a role in changing homocysteine into other amino acids for use by the body; so, it is possible that they might play a protective role in osteoporosis. Research is ongoing as to whether supplementation with these B vitamins might reduce fracture risk.” This paragraph is quoted from:
http://www.iofbonehealth.org/nutrition
The studies referred to are:
1. McLean RR, Jacques PF, Selhub J, et al. (2004) Homocysteine as a predictive factor for hip fracture in older persons. N Engl J Med 350:2042-49
2. Morris MS, Jacques PF, Selhub J (2005) Relation between homocysteine and B-vitamin status indicators and bone mineral density in older Americans. Bone 37:234-42
I take Nature's Bounty Sublingual Vitamin B12, 5000 mcg (5 mg) per microlozenge. I was using it three times per week, but I have recently increased my intake to the recommended dosage of one microlozenge daily. You dissolve these under your tongue for maximum absorption.
My multivitamin, Nature Made Multi For Her 50+, contains 6 mg of vitamin B6,25 mcg of vitamin B12, and 400 mcg of folic acid.
Wednesday, May 9, 2012
Effects of Strontium Citrate on Osteoblasts
The objective of this study was
to
assess the effects of strontium citrate on the proliferation and
differentiation of osteoblastic cells obtained from human alveolar bone.
Primary osteoblasts, obtained from human alveolar bone residues at the time of
third molar extractions and explanted in culture, were seeded in BGJb media containing
10% FCS. After the cells reached a semiconfluent stage, strontium citrate (bibasic
anhydrous, pure grade from Jost Chemical) at various concentrations
(0.05-1.0 mM) was added.
The MTT test showed the cells to be responsive to strontium
citrate with significant increases in cellular activity/proliferation at 24 and
48 hrs. Alkaline phosphatase activity was significantly enhanced at 48 and 72
hrs with strontium citrate concentrations in the test range.
The data support the hypothesis that strontium citrate
increases the proliferative/alkaline phosphatase activity of human osteoblastic
cells from alveolar bone. The results validate previous research that has been
done with other forms of strontium in clinical studies and rodent calvarial
cells and indicates that strontium citrate could be a promising agent in
treating oral as well as systemic bone disorders. Tuesday, April 24, 2012
Interpretation of BMD Scans in Patients Stopping Strontium Ranelate Treatment
“The oral administration of strontium ranelate causes a clinically significant overestimation of BMD because of the high attenuation of X-rays by strontium atoms in bone." GM Blake and I. Fogelman “performed a theoretical study to calculate the long-term effect of strontium treatment on BMD and establish the duration of past treatment for which the remaining bone strontium content (BSC) has a negligible effect on BMD.” “Estimates of the strontium BMD artefact after treatment has stopped were performed on the assumption that the BSC effect accounts for 75% of the total measured BMD change at 3 years.”
“If 75% of the BMD changes are explained by BSC, in the average patient, 3-year treatment leads to a spine BMD artefact of 11.2%, decreasing to 3.8% 10 years after stopping treatment. The BMD artefacts at the total hip and femoral neck sites are smaller by factors of 0.65 and 0.53, respectively.” “On average, 6-month treatment is required for the spine BMD artefact to exceed 3%, the figure adopted as the maximum BMD change caused by bone strontium that has a negligible effect on scan interpretation.”
The researchers concluded that “strontium ranelate treatment lasting for > 6 months can affect BMD measurements for many years afterward.”
http://www.ncbi.nlm.nih.gov/pubmed/16939400
J Bone Miner Res. 2006 Sep;21(9):1417-24.
Subscribe to:
Posts (Atom)
Wandering Skeleton

Artist: Joel Hoekstra
Osteoporotic Bone
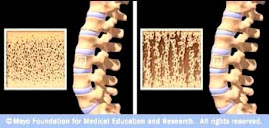
Source: www.mayoclinic.com