Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Showing posts with label Actonel. Show all posts

Friday, February 16, 2018

BMD Increases by Varying Amounts with Strontium Citrate and Decreases by Varying Amounts after Discontinuation


A study published September 13, 2016, presents three case studies of patients who took strontium citrate (680 mg strontium per day) for six years, five years, and four years (Cases 1, 2, and 3, respectively) and then stopped taking it for two years, one year, and one year (Cases 1, 2, and 3, respectively). The study gives the increases in BMD with SrC and the decreases when the supplement was discontinued.  Of note is the fact that both the increases and decreases vary with the site (lumbar spine or total hip), the individual, and the number of years of use or discontinuation of SrC. Also, keep in mind that stopping any of the osteoporosis drugs will also result in loss of some of the BMD gains because there is no cure for osteoporosis.

Case 1
A 76-year-old female with osteoporosis (OP) took alendronate weekly for 10 years till 2006, then every other week for another year and was initiated on a drug holiday. She started self-administrating SrC (680mg/day) in 2006 and continued to take daily calcium (600mg bid) and vitamin D (2000units). Serum calcium and Vitamin D (32-66ng/ml) remained normal. She continued SrC on her own till 2012, when she agreed to stop taking it due to concerns about accumulation and toxicity.

On dual-energy X-ray absorptiometry (DXA) scan, total hip mean BMD increased 2.7% in the first 2 years on SrC after stopping alendronate, and continued to increase to a maximum of 9.2% after 6 years of treatment with SrC (1.53%/year). Lumbar Spine (LS) BMD was non-diagnostic due to degenerative changes in the spine.

In the first 2 years off of SrC, total hip mean BMD decreased by 5.7%.

Case 2
A 64-year-old female with history of OP, which was diagnosed in 2001, took Actonel 35mg weekly for 5 years, stopped for more than a year and resumed Actonel intermittently for another 2 years before starting drug holiday. She was taking Calcium 500 mg in the multivitamin and 2500 mg of vitamin D. Serum calcium and vitamin D were within normal range. She started strontium citrate (680mg strontium) daily in 2009 and took it for 5 years, stopping it in 2014.

Yearly assessment of her BMD via DEXA scan showed an increase of 4.3% at LS spine (L1-L4 vertebrae), and 7.6 % at total hip within 1 year of SrC treatment. At 5 years, BMD increase was 6.5 % at LS and 12% for mean total hip. She agreed to stop SrC at this time.

One year after stopping SrC, LS BMD decreased by 9.1 % and total hip BMD decreased by 4.2%.

Case 3
A 59-year-old female with OP was treated with weekly alendronate for 4 years till 2007, when she stopped it due to concerns for osteonecrosis of jaw. She was advised to resume alendronate in 2008 due to declining BMD, but opted not to take it.

She started self-administration of 680mg of SrC daily in February 2009 and continued it for four years till January 2013, when she stopped it due to myalgias and concern about risk for toxicity. Due to her history of ulcerative colitis, she was limited in dairy intake, although she averaged half a cup of almond milk daily and took calcium supplements. Serum calcium and vitamin D were within normal range.

BMD via DEXA scan showed an increase of 10.7 % at LS (L1-L4) at 2 years after starting SrC, and 4.3 % at total hip.

BMD decreased by 14% at LS and by 6.4% at total hip a year after stopping SrC.

Mirza FS, Azim S, Bhargava A (2016) Change in Bone Mineral Density with Strontium Citrate: An Illusion or Reality. J Nutrition Health Food Sci 4(3): 1-3. DOI: http://dx.doi.org/10.15226/jnhfs.2016.00167

Tuesday, October 9, 2012

Case Study on Strontium Citrate for Osteoporosis with Fragility Fractures


Sara S. DeHart, MSN, Ph.D., is an 80-year-old woman who was diagnosed with osteopenia at age 63. She was treated initially with Fosamax 10 mg. daily and Estraderm patches twice weekly.  She discontinued the patches after about two years, and Fosamax after about three years. Following a fragility fracture of the sacrum, she was prescribed Actonel 5 mg five times a week. Her vitamin D blood level was found to be very low, although she had supplemented with 400 IU vitamin D3 throughout her adult life.
She followed “standards of care” medical recommendations until she developed a second fragility fracture at T9 while taking Actonel.  At that point, she stopped using Actonel and began taking strontium citrate. She increased her vitamin D3 supplementation. Today, she is 80 years old and her BMD is normal. More importantly, she has not fractured, even after a recent fall onto an asphalt driveway! Follow this link to read her amazing story:


Tuesday, April 7, 2009

FDA Bisphosphonate Alert

Information on Bisphosphonates (marketed as Actonel, Actonel+Ca, Aredia, Boniva, Didronel, Fosamax, Fosamax+D, Reclast, Skelid, and Zometa)

FDA ALERT [1/7/2008] - FDA is highlighting the possibility of severe and sometimes incapacitating bone, joint, and/or muscle (musculoskeletal) pain in patients taking bisphosphonates. Although severe musculoskeletal pain is included in the prescribing information for all bisphosphonates, the association between bisphosphonates and severe musculoskeletal pain may be overlooked by healthcare professionals, delaying diagnosis, prolonging pain and/or impairment, and necessitating the use of analgesics.

The severe musculoskeletal pain may occur within days, months, or years after starting a bisphosphonate. Some patients have reported complete relief of symptoms after discontinuing the bisphosphonate, whereas others have reported slow or incomplete resolution. The risk factors for and incidence of severe musculoskeletal pain associated with bisphosphonates are unknown.

This severe musculoskeletal pain is in contrast to the acute phase response characterized by fever, chills, bone pain, myalgias, and arthralgias that sometimes accompanies initial administration of intravenous bisphosphonates and may occur with initial exposure to once-weekly or once-monthly doses of oral bisphosphonates. The symptoms related to the acute phase response tend to resolve within several days with continued drug use.

Healthcare professionals should consider whether bisphosphonate use might be responsible for severe musculoskeletal pain in patients who present with these symptoms and consider temporary or permanent discontinuation of the drug.
This information reflects FDA's current analysis of data available to FDA concerning this drug. FDA intends to update this when additional information or analyses become available.

Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

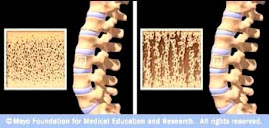
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.