Human Skeleton

Human Skeleton

WELCOME TO STRONTIUM FOR BONES BLOG

Have you experienced negative, and even dangerous, side effects from Fosamax (alendronate), Boniva (ibandronate), Actonel (risedronate), Reclast (zoledronic acid), Prolia (denosumab), Forteo (teriparatide), Tymlos (abaloparatide), or other drugs prescribed for osteoporosis? If you have, then rest assured there is a safe, effective treatment for this condition. Strontium, primarily in the form of strontium citrate, is taken orally once a day.

Visitors to my blog can leave comments or ask questions and can remain anonymous, if they wish. Their comments are relayed to my g-mail inbox. Below each post, the number of comments for that post is cited and underlined because it is a link. By clicking on that link below any post, a window opens so that a visitor can leave a comment. Ideally, visitors leave comments on posts most relevant to their comments. All comments to my posts are moderated by me.

Browse the posts and visit the link library of references.


Blog Archive

Thursday, December 11, 2014

Three Quarters of Hip Fracture Patients are Vitamin D Deficient


New Delhi researchers show that vitamin D levels may be a useful index for the assessment of hip fracture risk in elderly people.

A study in New Delhi India has revealed high rates of vitamin D deficiency among hip fracture patients, confirming the conclusions of similar international studies which point to vitamin D deficiency as a risk factor for hip fracture.

A group of 90 hip fracture patients was compared to a matched control group of similar age, sex and co-morbidity. Of the patients who had suffered hip fractures, 76.7% were shown to be vitamin D deficient as measured by serum 25(OH)D levels of less than 20 ng/ml. In addition, 68.9% had elevated PTH levels. In comparison, only 32.3% of the controls had vitamin D deficiency and 42.2% had elevated PTH levels (secondary hyperparathyroidism).

Vitamin D deficiency has been linked to the pathogenesis of osteoporosis and is increasingly thought to play a role in muscle strength, certain cancers, multiple sclerosis and diabetes. Vitamin D levels are very low in the Indian population in all age groups, and could be explained by skin pigmentation, traditional clothing and the avoidance of sunlight.

The results of the New Delhi study confirm that serum 25 (OH)D levels may be a useful index for the assessment of risk of hip fracture in elderly people.

The study (OC13) was presented at the IOF Regionals – 1st Asia-Pacific Regional Osteoporosis Meeting being held in Singapore from December 10-13, 2010.
 
All abstracts from the meeting have been published in Osteoporosis International, Vol. 21, Suppl. 5, 2010.
http://www.iofbonehealth.org/news/indian-study-reveals-three-quarters-hip-fracture-patients-are-vitamin-d-deficient

FRAX Identifies Women with Prevalent Asymptomatic Vertebral Fractures


Abstract

Background
A Moroccan model for the FRAX tool to determine the absolute risk of osteoporotic fracture at 10 years has been established recently. The study aimed to assess the discriminative capacity of FRAX in identifying women with prevalent asymptomatic vertebral fractures (VFs).

Methods
We enrolled in this cross-sectional study 908 post-menopausal women with a mean age of 60.9 years ±7.7 (50 to 91) with no prior known diagnosis of osteoporosis. Subjects were recruited from asymptomatic women selected from the general population. Lateral VFA (vertebral fracture assessment) images and scans of the lumbar spine and proximal femur were obtained using a GE Healthcare Lunar Prodigy densitometer. VFs were defined using a combination of Genantsemiquantitative (SQ) approach and morphometry. We calculated the absolute risk of major fracture and hip fracture with and without bone mineral density (BMD)using the FRAX website.The overall discriminative value of the different risk scores was assessed by calculating the areas under the ROC curve (AUC).

Results
VFA images showed that 179 of the participants (19.7%) had at least one grade 2/3 VF. The group of women with VFs had a statistically significant higher FRAX scores for major and hip fractures with and without BMD, and lower weight, height, and lumbar spine and hip BMD and T-scores than those without a VFA-identified VF. The AUC ROC of FRAX for major fracture without BMD was 0.757 (CI 95%; 0.718-0.797) and 0.736 (CI 95%; 0.695-0.777) with BMD, being 0.756 (CI 95%; 0.716-0.796) and 0.747 (CI 95%; 0.709-0.785), respectively for FRAX hip fracture without and with BMD. The AUC ROC of lumbar spine T-score and femoral neck T-score were 0.660 (CI 95%; 0.611-0.708) and 0.707 (CI 95%; 0.664-0.751) respectively.

Conclusion
In asymptomatic post-menopausal women, the FRAX risk for major fracture without BMD had a better discriminative capacity in identifying the women with prevalent VFs than lumbar spine and femoral neck T-scores suggesting its usefulness in identifying women in whom VFA could be indicated. 

To read the full research article by Abdellah El Maghraoui, Siham Sadni, Nabil Jbili, Asmaa Rezqi, Aziza Mounach and Imad Ghozlani click on this link:

 http://www.biomedcentral.com/1471-2474/15/365


Friday, December 5, 2014

Similarities in Acquired Factors Related to Postmenopausal Osteoporosis and Sarcopenia


“Sarcopenia, that is, muscle wasting, and osteoporosis,
that is, fragile bone disease, are significant health burdens
among the postmenopausal women. The prevalence of sarcopenia
has been reported to be 10% to 40% in postmenopausal
population depending on the reference method used and the population.
Osteoporosis affects approximately 30% of (the) female population
over 50 years (of age). Sarcopenia results in decline in activities of
daily living, quality of life, and self-rated health and increases falls and related
skeletal fractures which have been estimated to have deep impact of social
and healthcare-related costs of the postmenopausal population.”

“The present paper focuses on similarities in acquired
factors associated with postmenopausal osteoporosis and
sarcopenia concentrating on decades after the menopausal
transition. Consequently, essential aspects on the effects of
aging on sarcopenia and osteoporosis will be covered.”

“Postmenopausal women are at risk of both osteoporosis
and sarcopenia. There is evidence that these two conditions
coexists and share similar risk factors. Both sarcopenia
and osteoporosis are strongly linked not only to aging
but also to estrogen depletion and thereby to menopausal
transition. This makes the postmenopausal population a
significant target group for prevention of both sarcopenia
and osteoporosis.”

“While the associations between muscle strength, muscle
mass, and functional capacity with clinically relevant endpoint
of osteoporosis, that is, BMD and fractures, have been
reported, there are no studies addressing the associations
between three stages of clinical sarcopenia, that is, presarcopenia,
sarcopenia, and severe sarcopenia. The associations
of the three modalities of sarcopenia with osteopenia,
osteoporosis, and severe osteoporosis remain unexplored.
An essential part of the diagnosis of both osteoporosis
and sarcopenia includes DXA, which allows simultaneous
assessment of both conditions. The future research should
concentrate on exploring the clinically relevant dimensions
and interactions of sarcopenia and osteoporosis.”


To read the full review article by Joonas Sirola and Heikki Kröger:


Wandering Skeleton

Wandering Skeleton
Artist: Joel Hoekstra

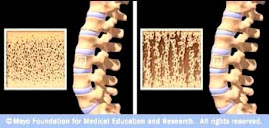
Osteoporotic Bone

Osteoporotic Bone
Source: www.mayoclinic.com

How Strontium Builds Bones

Strontium is a mineral that tends to accumulate in bone. Studies have shown that oral doses of strontium are a safe and effective way to prevent and reverse osteoporosis. Doses of 680 mg per day appear to be optimal. See my "For More Information About Strontium" links section.

Osteoporosis is caused by changes in bone production. In healthy young bones there is a constant cycle of new bone growth and bone removal. With age, more bone is removed and less new bone is produced. The bones become less dense and thus more fragile.

Scientists believe that strontium works in two ways. It may stimulate the replication of pre-osteoblasts, leading to an increase in osteoblasts (cells that build bone). Strontium also directly inhibits the activity of osteoclasts (cells that break down bone). The result is stronger bones.

When taking strontium, be sure to take 1200 mg calcium, 1000 IU vitamin D3, and 500 mg magnesium daily. It is best to take strontium late at night on an empty stomach. Calcium and strontium may compete with each other for absorption if taken together.