- A higher-protein diet that emphasizes lean meats and low-fat dairy foods as sources of protein and calcium can mean weight loss without bone loss. The evidence is in bone scans taken throughout a new University of Illinois study.
This is an important finding because many people, especially women in mid-life, are concerned with both obesity and osteoporosis. However, treating obesity often increases risk for osteoporosis because many people lose bone mass when they lose weight.
The research compared the results of a high-protein, dairy-intensive diet with a conventional weight-loss diet based on the food-guide pyramid.
Study co-author Donald Layman, a U of I professor of nutrition, has previously reported that protein-rich weight-loss diets preserve muscle mass, help lower blood sugar and lipids, and improve body composition by targeting weight carried in the abdomen.
In the recent study, Layman's diet prescribed approximately 30 percent of all calories from protein, with an emphasis on lean meats and low-fat dairy products.
The scientists recruited and randomized 130 middle-aged, overweight persons at two sites--the U of I and Pennsylvania State University. Participants then followed either the higher-protein weight-loss diet or a conventional higher-carbohydrate weight-loss diet based on the food-guide pyramid for four months of active weight loss followed by eight months of weight maintenance.
Essentially, lean meats and low-fat milk, cheese, yogurt, etc. were substituted for some of the high-carbohydrate foods in the food-pyramid diet. Participants also ate five servings of vegetables and two to three servings of fruit each day.
Bone mineral content and density were measured with DXA scans of the whole body, lumbar spine, and hip at the beginning of the study, at four months, at eight months, and at the end of the 12-month period.
In the higher-protein group, bone density remained fairly stable, but bone health declined over time in the group that followed the conventional higher-carbohydrate diet. A statistically significant treatment effect favored the higher-protein diet group.
The combination and/or interaction of dietary protein, calcium from dairy, and the additional vitamin D that fortifies dairy products appears to protect bone health during weight loss.
Because higher-protein diets have been associated with elevated urinary calcium levels, some scientists have feared that these diets cause bone demineralization.
The U of I team measured these levels at the beginning and eight months into the study. Although the researchers did note increased amounts of urinary calcium in the higher-protein group, they attributed the source of the increased calcium to improved intestinal absorption of calcium rather than bone loss.
Other recent studies using radio-labeled calcium have shown that the higher urinary calcium levels associated with higher-protein diets are not coming from bone as some researchers had believed.
https://www.sciencedaily.com/releases/2008/06/080605113006.htm
Human Skeleton

Showing posts with label urinary calcium. Show all posts
Showing posts with label urinary calcium. Show all posts
Saturday, June 19, 2021
How to Lose Weight Without Losing Bone


Monday, January 5, 2015
Salt and osteoporosis
Introduction
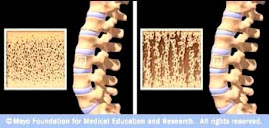
Osteoporosis is a condition involving the thinning of bones (bone demineralization), leaving them brittle and more susceptible to fracture. Ninety nice percent of calcium is stored in the bones, so sufficient calcium is important in order to maintain or reach peak bone mass (PBM).In the UK, an estimated 3 million people are suffering from osteoporosis, with 1 in 2 women and 1 in 3 men over 50 years old breaking a bone at least once, mainly due to poor bone health. Each month, 1,150 people die as a result of a hip fracture. Osteoporosis mainly effects the older population, with 19.8 million people over the age of 50 in the UK. Since the 1960’s there has been a 7 fold increase in the number of osteoporosis cases. Each year osteoporosis costs the NHS approximately 2.3 billion pounds.
Who is most at risk of osteoporosis?
The older population are more at risk of osteoporosis because bones naturally become thinner as we get older. Post-menopausal women are particularly at risk of osteoporosis because of the decrease in the female hormone, estrogen. Those with higher salt intakes are increasing the amount of bone demineralization that takes place.Studies have also demonstrated that there is a correlation between salt intake and calcium excretion in young and adolescent girls. It has been suggested that this may result in a reduced peak bone mass, which would increase the risk of osteoporosis later in life. Consuming a low salt diet during adolescent years may therefore be important, to reduce the risk of osteoporosis later in life.
How does Salt Contribute?
Studies dating back to the 1980’s have found possible links between salt intake and urinary calcium (Ca) excretion.
 Figure 1 – Changes in hip bone density with different urinary sodium excretions. |
A high salt intake increases calcium losses in the urine (calciuria), some
of which will be directly from the bones. One study found that for each
100mmol increase in salt intake, urinary Ca is increased by 1.4mmol. If
this loss is assumed to be from the bone, then this equates to about 1% extra
loss of bone each year. Over extended periods this would lead to
the weakening of bones and ultimately osteoporosis. Both epidemiological studies and randomized trials have shown that a decrease in salt intake reduces urinary calcium excretion. A study in post-menopausal women showed that the loss of hip bone density over 2 years was related to 24-hour urinary sodium at entry to the study, and was as strong as that relating to calcium intake. It was calculated that a reduction in salt intake from 10 to 5 g/day would have the same effect on hip bone density as an increase in calcium intake of 1000mg/day, a difficult amount to achieve without resorting to supplements (Fig 1). Another study has suggested that in postmenopausal women with a sodium intake of more than or equal to 3.4g/day (8.5g salt), a reduction in salt intake would benefit their bone health. |
Blood Pressure, Osteoporosis and Kidney StonesSalt intake and blood pressure are strongly linked, and it is also believed that patients with high blood pressure excrete more calcium in the urine and are, therefore, at higher risk of osteoporosis and kidney stones. Recently, a study showed sodium to be a major linking factor between blood pressure and osteoporosis. The authors found that hip and spine Bone Mass Density (BMD) were inversely correlated with a higher sodium excretion, i.e. the higher the salt intake, the lower the BMD. They concluded that the increase in calcium excretion is obligatory as a result of the increased sodium in the diet (Fig 2). Another study showed that a 20mmHg increase in BP is associated with 0.28mmol/day increase in Urinary Ca. |

Figure 2 – the link
between salt intake, blood pressure and bone mineral loss.
|
Current Salt Intake & Dietary Advice
Almost everyone in the UK (and the rest of the Western world) eats too much salt. The daily recommended amount in the UK is no more than 6 grams a day; the current average salt intake is 8.6g salt a day although many people are eating more than this.People with or considered at risk of osteoporosis should ensure that they keep their salt intake below the recommended maximum of 6g. This can be achieved by simple changes, such as consuming less processed foods and checking product labels before purchase. Consuming low salt dairy products such as milk will also help maintain bone mass. Caffeine and fizzy drinks are thought to reduce bone mass, and therefore should be kept to a minimum. An increase in Vitamin D, Zinc and Copper may also be of help.
The original article with references is available here:
Also see my next post, "Americans Consume Too Much Sodium (Salt)," for information about salt intake in the U.S.A.
Subscribe to:
Posts (Atom)
Wandering Skeleton

Artist: Joel Hoekstra
Osteoporotic Bone
Source: www.mayoclinic.com